
Emma Hanegraef
Emma holds a MSc in Cellular and Genetic Engineering and has been passionate about the science behind skincare and health since the age of 12. As an experienced formulator, she translates complex scientific concepts into accessible knowledge, helping you make informed choices about your formulas.
GLP-1 medicines have changed how people talk about weight. Millions now use drugs like semaglutide and tirzepatide, and the number on the scale drops fast for many of them. Yet weight is only one signal. Metabolic health is about how your body handles sugar, fat and energy every day, and a lower weight does not guarantee healthy numbers on the inside.
The gap is large. A 2022 analysis of US national data found that only 6.8% of adults had optimal cardiometabolic health across weight, blood sugar, blood lipids, blood pressure and heart disease [1]. Most adults fell short in at least one area.
This guide looks past kilograms. You will learn:
- What metabolic health means, which markers to check, and the signs of poor metabolic health
- What GLP-1 is, how the natural hormone works, and what the drugs change
- How oxidative stress, inflammation and your gut affect your metabolism
- How to improve metabolic health naturally, including foods that support your own GLP-1
- What to eat while taking GLP-1, and whether GLP-1 supplements work
- What human studies on astaxanthin report so far, as a separate and emerging field of research
This article is for information only. If you take a GLP-1 medicine or manage a metabolic condition, talk to your doctor before you change your diet or add a supplement.
What Is Metabolic Health?
Metabolic health means your blood sugar, blood fats, blood pressure and waist size sit in healthy ranges without medication. It describes how well your body turns food into energy and stores the rest.
Your weight tells you how much you carry. It does not tell you where fat sits, how much muscle you have, or how your blood vessels cope. Two people with the same weight can have very different results on a blood test.
That is why doctors look at a cluster of measurements. When three or more of them fall outside healthy ranges, clinicians call it metabolic syndrome. International heart and diabetes organisations agreed on a shared set of five risk factors in 2009 [2], and the markers table below uses them.
Why the scale misses part of the picture
- Fat around your organs, called visceral fat, affects blood sugar and blood fats more than fat under the skin.
- Muscle is your largest site for glucose uptake after a meal. Losing muscle can weaken that control.
- Blood pressure and cholesterol can rise with age even when weight stays flat.
- Oxidative stress and low-grade inflammation do not show on a scale, yet they track with poor metabolic markers.
Signs of poor metabolic health
Poor metabolic health is often silent. Most signs show up on a tape measure, a blood pressure cuff or a blood test, not in how you feel.
- Your waist keeps growing, even if your weight looks stable.
- Your blood pressure reads 130/85 mmHg or higher.
- Your fasting glucose or HbA1c sits at the top of the normal range or above it.
- Your triglycerides are high and your HDL cholesterol is low.
- You notice darker, velvety skin patches on your neck or in your armpits. Doctors link this to insulin resistance.
If one or more of these apply, ask your doctor for a full check. Early changes are easier to reverse.
Metabolic Health Markers That Matter More Than Weight
Five markers define metabolic health in most clinical guidelines. Two more add useful detail. Ask your doctor for these at your next check-up.
|
Marker |
What it shows |
Common risk threshold |
|---|---|---|
|
Fasting blood glucose |
Sugar in your blood after an overnight fast |
5.6 mmol/L (100 mg/dL) or higher |
|
HbA1c |
Your average blood sugar over about 3 months |
5.7% (39 mmol/mol) or higher signals prediabetes |
|
Triglycerides |
Fat carried in your blood after you eat and store energy |
1.7 mmol/L (150 mg/dL) or higher |
|
HDL cholesterol |
The particles that carry cholesterol back to the liver |
Below 1.0 mmol/L in men, below 1.3 mmol/L in women |
|
Blood pressure |
Force on your artery walls |
130/85 mmHg or higher |
|
Waist circumference |
A proxy for visceral fat |
94 cm or more in European men, 80 cm or more in European women |
|
LDL and oxidized LDL |
Cholesterol particles; the oxidized form drives plaque |
LDL targets depend on your overall risk |
The glucose, lipid, blood pressure and waist thresholds follow the joint international definition of metabolic syndrome [2]. The HbA1c range follows the American Diabetes Association [3]. Your doctor may use different targets based on your history.
Blood sugar and insulin sensitivity
Fasting glucose gives a single snapshot. HbA1c shows the trend over weeks. Insulin sensitivity tells you how hard your body works to keep glucose in range. If your pancreas must release more and more insulin, your glucose can look normal for years before it rises.
Triglycerides and HDL
High triglycerides with low HDL is a common pattern in insulin resistance. Many doctors read the two together. A falling triglyceride level is one of the first changes people see when their metabolism improves.
LDL and oxidized LDL
LDL carries cholesterol to your tissues. When LDL particles react with free radicals, they become oxidized. Oxidized LDL is taken up by cells in the artery wall, and this process plays a part in plaque formation. Standard blood tests report LDL, but not oxidized LDL. Research studies often measure both.
Blood pressure and waist size
Blood pressure reflects the health of your blood vessels. Waist size is a simple way to estimate visceral fat. Measure it at the level of your belly button, after you breathe out.
What Is GLP-1 and How Does It Work?
GLP-1, short for glucagon-like peptide-1, is a hormone your gut makes every time you eat. GLP-1 medicines are built to copy it. To understand the drugs, start with the hormone.
The GLP-1 hormone
Special cells in your intestine, called L-cells, release GLP-1 when food reaches them [4]. The hormone sends signals to your pancreas, your stomach and your brain. Your body breaks it down within minutes, so its effect is short and tied to each meal [4].
How GLP-1 works on your metabolism
GLP-1 has four main jobs after a meal [4]:
- It helps your pancreas release insulin when blood sugar rises.
- It lowers glucagon, a hormone that tells your liver to release more sugar.
- It slows how fast your stomach empties, so sugar enters your blood more gradually.
- It signals fullness to your brain, which reduces how much you eat.
GLP-1 medicines resist that fast breakdown. They stay active for hours or days, which makes the effects much stronger and longer than your own hormone can produce.
GLP-1 and gut health
Your gut is where GLP-1 starts, so gut health and metabolic health are closely linked. The trillions of microbes in your gut, your gut microbiome, affect how you process food, store fat and handle blood sugar. Researchers now see the microbiome as a factor in metabolic health, although most findings still show links rather than proof of cause [5].
One link is better understood. Gut microbes ferment fibre into short-chain fatty acids. In human colon cells, one of these acids, propionate, triggered the release of GLP-1 [6]. In a 24-week trial, overweight adults who took a fibre built to release propionate in the colon gained less weight and less abdominal fat than a control group [6].
So what? What you feed your gut microbes may shape your own GLP-1 response. Our article on gut health explains how your gut and your wider health connect.

GLP-1 Beyond Weight Loss: What Changes and What Stays Open
GLP-1 drugs do more than lower weight. Many people also see better blood sugar, lower blood pressure and lower triglycerides. That is why doctors now talk about GLP-1 and metabolic health together.
What the large trials show
- In the STEP 1 trial, adults on weekly semaglutide lost about 15% of their body weight over 68 weeks [7].
- The SELECT trial followed over 17,000 adults with overweight or obesity and existing heart disease, without diabetes. Semaglutide lowered major cardiovascular events by 20% compared with placebo [8].
These are real gains. They also leave three questions open.
1. Muscle goes with the fat
Fast weight loss takes some muscle with it. In a STEP 1 subgroup scanned with DXA, lean mass made up close to 40% of the weight lost [7]. Lean mass includes more than muscle, but the trend matters. Muscle clears glucose from your blood. Less muscle can mean less metabolic reserve as you age.
2. The gains depend on staying on the drug
In the STEP 1 extension, people who stopped semaglutide regained about two-thirds of the weight they had lost within a year [9]. Most of their cardiometabolic improvements moved back toward where they started. Habits built during treatment are what you keep when treatment ends.
3. Weight loss does not address every pathway
GLP-1 drugs act mainly through appetite, insulin release and slower stomach emptying. Oxidative stress, inflammation, the quality of your diet and your fitness level are separate levers. Losing weight often improves them. It does not replace them.
So what? Use the scale as one data point. Track your blood results, protect your muscle and build habits that last beyond the prescription.
Oxidative Stress, Inflammation and Metabolic Health
Two processes run in the background of most metabolic problems. Neither shows up on a scale, and neither is part of a standard blood test.
Oxidative stress and metabolic health
Your cells make free radicals, also called reactive oxygen species, as they turn food into energy. Your antioxidant defences normally keep them in check. Oxidative stress is what happens when free radicals outpace those defences. They then damage fats, proteins and DNA.
Researchers measure this damage with markers like malondialdehyde and isoprostanes. Both come from oxidized fats. Excess calories, high blood sugar and visceral fat all raise free radical production.
Oxidative stress and insulin resistance
Oxidative stress also affects how your cells respond to insulin. In a study of cell models and obese mice, higher levels of reactive oxygen species triggered insulin resistance, and lowering them improved insulin sensitivity [10]. This was lab research, not a human trial. It helps explain why scientists study oxidative stress as a part of metabolic health.
Inflammation and metabolic health
Your immune system and your metabolism work closely together. When fat tissue grows, especially around your organs, it releases signals that keep your immune system switched on at a low level. This chronic inflammation affects metabolism and is linked to obesity, type 2 diabetes and heart disease [11].
Doctors measure it with high-sensitivity C-reactive protein, or hs-CRP. A level above 3 mg/L points to higher cardiovascular risk. Learn more on our anti-inflammatory benefits page.
Antioxidants and metabolic health
Your body makes its own antioxidant enzymes, and it also takes antioxidants from food. Colourful vegetables, berries, herbs, olive oil and algae all supply them. Carotenoids, the pigments that make foods red, orange and yellow, are one group researchers study closely.
Not all antioxidants work the same way. Some protect the watery parts of cells, some protect fats, and a few cover both. Our guide to the most potent antioxidant compares them.
So what? Weight loss lowers some of this background load. Food quality, activity and sleep matter too.
How to Improve Metabolic Health Naturally
The basics have the strongest evidence. They work with or without medication, and they keep working after treatment ends.
A metabolic health diet
There is no single metabolic health diet. The patterns with the best evidence share a few traits. They are built on whole foods, rich in fibre and plants, with enough protein and few ultra-processed foods.
Foods for metabolic health
- Vegetables and legumes, such as beans, lentils, chickpeas, leafy greens and cruciferous vegetables
- Whole grains, such as oats, barley, rye and wholegrain bread
- Protein foods, such as fish, eggs, yoghurt, poultry, tofu and legumes
- Healthy fats, such as olive oil, nuts, seeds and oily fish
- Colourful fruit, such as berries, citrus and other whole fruit rather than juice
- Fermented foods, such as plain yoghurt, kefir and sauerkraut, for gut diversity
Aim for at least 25 g of fibre a day. Increase it slowly and drink enough water.

How to increase GLP-1 naturally
Your own GLP-1 response is far weaker than a GLP-1 drug. Still, the food you eat and the order you eat it in can raise it.
- Fibre and GLP-1. Your gut microbes ferment fibre into short-chain fatty acids, which can trigger GLP-1 release [6]. Legumes, oats, barley and vegetables are good sources.
- Protein and GLP-1. Protein is a strong trigger for GLP-1. In 15 adults with type 2 diabetes, 50 g of whey protein before breakfast raised GLP-1 and lowered blood sugar after the meal by 28% [12].
- Food order. In 16 adults with type 2 diabetes, eating protein and vegetables first and carbohydrates last raised GLP-1 and lowered the blood sugar rise by 53%, compared with carbohydrates first [13].
These studies were small and short, and most involved people with type 2 diabetes. The approach is simple and low-risk, so it is easy to try at home.
Daily habits that move your markers
- Lift weights two to three times a week. Resistance training is the main way to keep muscle while you lose fat. The World Health Organization advises muscle-strengthening work on at least two days a week for adults [14].
- Move every day. Aim for 150 to 300 minutes of moderate activity a week [14]. Short bouts of light walking that break up long periods of sitting lower the rise in blood sugar after meals [15].
- Sleep seven hours or more. Short sleep raises appetite hormones and lowers insulin sensitivity the next day.
- Get tested once or twice a year. Ask for fasting glucose, HbA1c, a full lipid panel and blood pressure. Measure your waist at home.
Common mistakes to avoid
- Judging progress by weight alone
- Cutting protein along with calories
- Skipping strength training because cardio feels easier
- Stopping medication without a plan for the habits that replace it
- Adding supplements before you know your baseline numbers
Nutrition While Taking GLP-1: What to Eat
GLP-1 drugs cut your appetite, so you eat less of everything. That includes protein, fibre, vitamins and minerals. In 2025, four US nutrition and obesity societies published joint advice on nutrition during GLP-1 treatment [16]. Their main concerns were stomach side effects, nutrient gaps from eating less, and loss of muscle and bone [16].
Your nutritional needs on GLP-1
- Protein first. Start each meal with your protein source, so you get it in before you feel full. Ask a dietitian to set a daily target for your body size.
- Fibre and fluids. Fibre and enough water help with constipation, a common side effect. Add fibre gradually.
- Nutrient-dense foods. When portions shrink, every bite counts. Choose vegetables, fruit, legumes, fish, eggs, dairy and whole grains over snacks and sweets.
- Vitamins and minerals. Eating less raises the risk of low iron, calcium, vitamin D and B12. Your doctor can check your levels.
- Strength training. The joint advice pairs diet with resistance training to protect muscle and bone [16].
What to eat on GLP-1 when your stomach is sensitive
- Eat small meals and stop when you feel full.
- Choose lower-fat cooking methods, such as baking, grilling or steaming. Rich, greasy meals often make nausea worse.
- Eat slowly and chew well.
- Drink fluids between meals rather than with large meals.
- Limit alcohol and very sugary drinks.
The joint advice also recommends support from a registered dietitian during treatment [16]. If you can, book a session when you start.
Do GLP-1 Supplements Work?
No supplement has been shown to match the effect of a GLP-1 medicine. Products sold as natural GLP-1 supplements or GLP-1 boosters usually contain fibres, plant extracts or probiotics. Some of these ingredients may nudge your own GLP-1 release. None act like a drug that stays active for days.
The evidence behind these claims is often thin. Even in the propionate study described above, the effect came from a fibre designed in a lab to release propionate in the colon, tested against a standard fibre [6]. The 2025 joint nutrition advice lists the dietary modulation of your own GLP-1 as an area that still needs more research [16].
How to judge a GLP-1 booster
- Check whether the product itself, not just one ingredient, was tested in people.
- Look at the dose. Lab and animal studies often use far more than a capsule contains.
- Be wary of before-and-after weight claims. Supplements in the EU cannot claim to treat or prevent disease.
- Food-first strategies, such as fibre, protein and food order, have a stronger evidence base and cost less.
Metabolic health supplements in context
Supplements cannot replace diet, activity, sleep or medication. Some have human research behind them for specific markers, but effects are usually modest. Treat them as a possible addition to a healthy routine, and check with your doctor first. The rest of this article looks at one of them, astaxanthin, and what the human research does and does not show.
Astaxanthin and Metabolic Health: What the Human Research Shows
Astaxanthin has been tested in randomised, placebo-controlled human trials on blood lipids, oxidative stress, body fat and fat use during exercise. Across these studies, the strongest and most consistent results appear in blood fats and oxidative stress markers. Astaxanthin research is a separate field from GLP-1 research, and no study has tested the two together.
What astaxanthin is
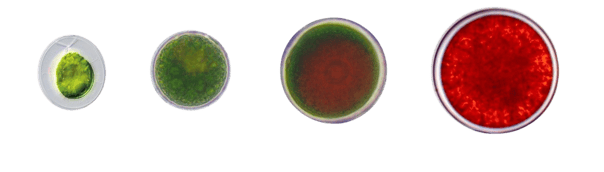
Astaxanthin is a red carotenoid made by the microalga Haematococcus pluvialis. It sits across the full width of cell membranes, which lets it neutralise free radicals on both the inner and outer surface. That position is why researchers study it in conditions linked to oxidative stress.
What the human trials measured
|
Study |
Who took part |
Dose and length |
What the researchers reported |
|---|---|---|---|
|
Ciaraldi et al., 2023 [17] |
34 adults with prediabetes and raised blood lipids |
12 mg a day, 24 weeks |
Lower LDL and total cholesterol; lower fibrinogen and fetuin-A; a trend toward better insulin action that did not reach significance |
|
Mashhadi et al., 2018 [18] |
44 adults with type 2 diabetes |
8 mg a day, 8 weeks |
Higher adiponectin; lower visceral fat, triglycerides, fructosamine and systolic blood pressure |
|
Choi et al., 2011 [19] |
27 adults with overweight or obesity |
20 mg a day, 12 weeks |
Lower LDL and ApoB; lower malondialdehyde and isoprostanes; higher antioxidant capacity |
|
Choi et al., 2011 [20] |
23 adults with overweight or obesity |
5 or 20 mg a day, 3 weeks |
Lower lipid peroxidation markers; higher superoxide dismutase activity |
|
Yoshida et al., 2010 [21] |
61 adults with mildly raised triglycerides |
6, 12 or 18 mg a day, 12 weeks |
Lower triglycerides at 12 and 18 mg; higher HDL at 6 and 12 mg; higher adiponectin |
|
Saeidi et al., 2023 [22] |
68 men with obesity |
20 mg a day, 12 weeks, with or without training |
Better lipid profile and body composition; largest change when astaxanthin was combined with training |
Astaxanthin and lipid metabolism
Blood fats show the clearest results. A 2024 meta-analysis pooled the controlled trials and found that astaxanthin, compared with placebo [23]:
- lowered triglycerides by 0.46 mmol/L, about 40 mg/dL
- raised HDL cholesterol by 0.13 mmol/L
- lowered total cholesterol by 0.22 mmol/L and LDL by 0.11 mmol/L
- lowered fasting insulin
The single trials point the same way. In adults with mildly raised triglycerides, 12 and 18 mg a day lowered triglycerides, and 6 and 12 mg a day raised HDL [21]. In adults with prediabetes and raised lipids, 12 mg a day for 24 weeks lowered LDL by 0.33 mmol/L, along with total cholesterol and markers of cardiovascular risk [17].
Astaxanthin, body fat and fat use
Several trials looked at fat stores and how the body burns fat. In adults with type 2 diabetes, 8 mg a day for 8 weeks reduced visceral fat and raised adiponectin, a hormone made by fat tissue that supports insulin sensitivity [18]. In men with obesity, 20 mg a day combined with training reduced body fat percentage more than training alone [22].
A 2026 crossover trial in 20 active women found that 12 mg a day for 2 weeks shifted the body toward burning more fat during moderate cycling [25]. Earlier studies in men gave mixed results, so this is an area to watch. Read more in our guide to astaxanthin and fat metabolism.
Astaxanthin, blood sugar and insulin sensitivity
In adults with type 2 diabetes, astaxanthin lowered fructosamine, a marker of blood sugar over 2 to 3 weeks [18]. In adults with prediabetes, insulin action trended toward improvement over 24 weeks [17]. Pooled data show a drop in fasting insulin [23] and in fasting glucose in type 2 diabetes [24]. Blood sugar is a newer focus than lipids, and larger trials will show how strong these effects are.
Astaxanthin and oxidative stress
The oxidative stress results are the largest in size. In adults with overweight or obesity, 3 weeks of astaxanthin lowered malondialdehyde by about 35% and isoprostanes by about 65% compared with baseline, while the activity of the antioxidant enzyme superoxide dismutase rose by about 190% [20]. A 12-week placebo-controlled trial confirmed lower oxidation markers and higher antioxidant capacity [19].
Astaxanthin and the gut microbiome
Research on astaxanthin and gut health is at the lab stage, but the early findings are promising. In a model that simulates the human colon, astaxanthin increased beneficial bacteria and the production of short-chain fatty acids [26]. In mice on a high-fat diet, an astaxanthin ester protected the gut barrier and increased beneficial bacteria such as Akkermansia and Lactobacillus [27]. Human trials on the microbiome are the next step.
What this means for you
- Astaxanthin has its strongest human evidence for blood fats and oxidative stress.
- Studies on body fat, fat use and blood sugar point in a positive direction.
- Gut microbiome findings come from lab and animal models so far.
- Most trials used 6 to 20 mg a day for 3 to 24 weeks, and most had fewer than 70 people.
Astaxanthin is fat-soluble, so take it with a meal that contains fat. It supports a healthy routine and does not replace medication. If you take any prescription medicine, check with your doctor or pharmacist first.
Why Astaxanthin Quality Matters in Metabolic Research
Human trials can only be compared when the ingredient is consistent. Natural astaxanthin varies in purity and stability depending on how the algae are grown.
- Open ponds expose algae to weather, dust and other organisms.
- Tubular and closed systems reduce contamination but vary in light and temperature control.
- Flat-panel photobioreactors give every cell even light in a sealed space.
axabio® grows Haematococcus pluvialis in a patented 4th-generation flat-panel photobioreactor in Hemiksem, Belgium. The closed system controls light, temperature and nutrients for each batch. The result is natural astaxanthin built for purity and stability, from the same strain in the same conditions every time. In 2026, axabio® became the first natural astaxanthin producer certified as a B Corporation, recognised for lower energy and water use relative to the purity achieved.
For you, this means fewer variables. When you choose a supplement, look for the algae source, the production method and third-party testing on the label. Our guide to the four generations of astaxanthin production explains the differences in detail.

Metabolic Health Is More Than a Number on the Scale
GLP-1 drugs have made weight loss more reachable for many people. Metabolic health asks a wider question. How do your blood sugar, blood fats, blood pressure, waist and muscle look today?
- Track your blood results, not only your weight.
- Protect your muscle with strength training and protein.
- Feed your gut with fibre, and put protein and vegetables first on your plate.
- Build habits you can keep if your treatment changes.
- Treat supplement research as early science and read it with care.
Astaxanthin stands out among the compounds researchers study in this field, with controlled human trials showing better blood fats and lower oxidative stress, and early work on fat use and the gut. Explore the science in the axabio® Knowledge Hub, and talk to your doctor about the markers that matter for you.

References
- O'Hearn M, Lauren BN, Wong JB, Kim DD, Mozaffarian D. Trends and disparities in cardiometabolic health among U.S. adults, 1999-2018. J Am Coll Cardiol. 2022;80(2):138-151. doi:10.1016/j.jacc.2022.04.046
- Alberti KG, Eckel RH, Grundy SM, et al. Harmonizing the metabolic syndrome: a joint interim statement of the International Diabetes Federation Task Force on Epidemiology and Prevention; National Heart, Lung, and Blood Institute; American Heart Association; World Heart Federation; International Atherosclerosis Society; and International Association for the Study of Obesity. Circulation. 2009;120(16):1640-1645. doi:10.1161/CIRCULATIONAHA.109.192644
- American Diabetes Association Professional Practice Committee. 2. Diagnosis and classification of diabetes: Standards of Care in Diabetes 2026. Diabetes Care. 2026;49(Suppl 1):S27-S49. doi:10.2337/dc26-S002
- Holst JJ. The physiology of glucagon-like peptide 1. Physiol Rev. 2007;87(4):1409-1439. doi:10.1152/physrev.00034.2006
- Fan Y, Pedersen O. Gut microbiota in human metabolic health and disease. Nat Rev Microbiol. 2021;19(1):55-71. doi:10.1038/s41579-020-0433-9
- Chambers ES, Viardot A, Psichas A, et al. Effects of targeted delivery of propionate to the human colon on appetite regulation, body weight maintenance and adiposity in overweight adults. Gut. 2015;64(11):1744-1754. doi:10.1136/gutjnl-2014-307913
- Wilding JPH, Batterham RL, Calanna S, et al. Once-weekly semaglutide in adults with overweight or obesity. N Engl J Med. 2021;384(11):989-1002. doi:10.1056/NEJMoa2032183
- Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and cardiovascular outcomes in obesity without diabetes. N Engl J Med. 2023;389(24):2221-2232. doi:10.1056/NEJMoa2307563
- Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension. Diabetes Obes Metab. 2022;24(8):1553-1564. doi:10.1111/dom.14725
- Houstis N, Rosen ED, Lander ES. Reactive oxygen species have a causal role in multiple forms of insulin resistance. Nature. 2006;440(7086):944-948. doi:10.1038/nature04634
- Hotamisligil GS. Inflammation and metabolic disorders. Nature. 2006;444(7121):860-867. doi:10.1038/nature05485
- Jakubowicz D, Froy O, Ahrén B, et al. Incretin, insulinotropic and glucose-lowering effects of whey protein pre-load in type 2 diabetes: a randomised clinical trial. Diabetologia. 2014;57(9):1807-1811. doi:10.1007/s00125-014-3305-x
- Shukla AP, Andono J, Touhamy SH, et al. Carbohydrate-last meal pattern lowers postprandial glucose and insulin excursions in type 2 diabetes. BMJ Open Diabetes Res Care. 2017;5(1):e000440. doi:10.1136/bmjdrc-2017-000440
- World Health Organization. WHO guidelines on physical activity and sedentary behaviour. Geneva: World Health Organization; 2020. ISBN 9789240015128
- Buffey AJ, Herring MP, Langley CK, et al. The acute effects of interrupting prolonged sitting time in adults with standing and light-intensity walking on biomarkers of cardiometabolic health in adults: a systematic review and meta-analysis. Sports Med. 2022;52(8):1765-1787. doi:10.1007/s40279-022-01649-4
- Mozaffarian D, Agarwal M, Aggarwal M, et al. Nutritional priorities to support GLP-1 therapy for obesity: a joint Advisory from the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society. Am J Clin Nutr. 2025;122(1):344-367. doi:10.1016/j.ajcnut.2025.04.023
- Ciaraldi TP, Boeder SC, Mudaliar SR, Giovannetti ER, Henry RR, Pettus JH. Astaxanthin, a natural antioxidant, lowers cholesterol and markers of cardiovascular risk in individuals with prediabetes and dyslipidaemia. Diabetes Obes Metab. 2023;25(7):1985-1994. doi:10.1111/dom.15070
- Mashhadi NS, Zakerkish M, Mohammadiasl J, Zarei M, Mohammadshahi M, Haghighizadeh MH. Astaxanthin improves glucose metabolism and reduces blood pressure in patients with type 2 diabetes mellitus. Asia Pac J Clin Nutr. 2018;27(2):341-346. doi:10.6133/apjcn.052017.11
- Choi HD, Youn YK, Shin WG. Positive effects of astaxanthin on lipid profiles and oxidative stress in overweight subjects. Plant Foods Hum Nutr. 2011;66(4):363-369. doi:10.1007/s11130-011-0258-9
- Choi HD, Kim JH, Chang MJ, Kyu-Youn Y, Shin WG. Effects of astaxanthin on oxidative stress in overweight and obese adults. Phytother Res. 2011;25(12):1813-1818. doi:10.1002/ptr.3494
- Yoshida H, Yanai H, Ito K, et al. Administration of natural astaxanthin increases serum HDL-cholesterol and adiponectin in subjects with mild hyperlipidemia. Atherosclerosis. 2010;209(2):520-523. doi:10.1016/j.atherosclerosis.2009.10.012
- Saeidi A, Nouri-Habashi A, Razi O, et al. Astaxanthin supplemented with high-intensity functional training decreases adipokines levels and cardiovascular risk factors in men with obesity. Nutrients. 2023;15(2):286. doi:10.3390/nu15020286
- Wan S, Wu W, Zhang Y, et al. Antioxidant lipid supplement on cardiovascular risk factors: a systematic review and meta-analysis. Nutrients. 2024;16(14):2213. doi:10.3390/nu16142213
- Shokri-Mashhadi N, Baechle C, Schiemann T, et al. Effects of carotenoid supplementation on glycemic control: a systematic review and meta-analysis of randomized clinical trials. Eur J Clin Nutr. 2025;79(2):113-125. doi:10.1038/s41430-024-01511-y
- Barker GA, Starkey JN, O'Neal EK, Waldman HS. Astaxanthin supplementation lowers respiratory exchange ratio during submaximal cycling in females: a randomized, double-blind, placebo-controlled crossover trial. J Diet Suppl. 2026;23(5):639-652. doi:10.1080/19390211.2026.2705844
- Zhang W, Sun H, Zhou J, Cong P, Tang Q. Investigating the impact of astaxanthin yogurt on gut microbiota and microbiota-mediated astaxanthin conversion using the SHIME® model. Food Funct. 2026;17(9):4201-4212. doi:10.1039/d5fo04878h
- Li X, Jing B, Xia C, Duan J, Zhang T, Li H, Che H. Multiomics dissection of the mechanisms underlying eicosapentaenoic acid astaxanthin ester-mediated protection against high-fat diet-induced gut barrier injury. J Agric Food Chem. 2026;74(31):24263-24276. doi:10.1021/acs.jafc.5c16899